What is CTE and how is it linked to repeated head impacts?
Chronic traumatic encephalopathy, or CTE, is a progressive neurodegenerative brain disease caused by repetitive brain trauma, including concussive and sub-concussive impacts [1, 2]. In sport, the concern is not only diagnosed concussion, but the cumulative effect of repeated sub-concussive head impacts that transmit force to the brain over time [1, 2, 3].
Read the full scientific explainer: CTE in Sport: How Sub-Concussions and Rotational Forces Affect the Brain.
Historically, CTE has been confirmed through post-mortem examination of brain tissue [4]. but advanced neuroimaging, clinical evaluation and cognitive assessment can identify objective evidence of chronic and progressive brain injury in living patients [5].
What does CTE stand for?
CTE stands for chronic traumatic encephalopathy.
Chronic Traumatic Encephalopathy (CTE) is a progressive neurodegenerative condition of the brain. It is caused by repetitive brain trauma, including repeated concussions and sub-concussions [1, 2]. A player may experience hundreds or thousands of sub-concussive head impacts across training and competition without being diagnosed with concussion. The growing scientific concern is that cumulative exposure to these sub-concussion impacts contributes to long-term changes in the brain [1, 2, 3].
The correlation between dementia and repetitive head impacts has been observed for a Century [6]. Before CTE was a known medical condition, “Punch Drunk” was a recognised complication of boxing in 1928 [6]. The term chronic traumatic encephalopathy was later introduced to describe progressive neurological deterioration associated with repetitive blows to the head [6]. It described severe mood changes, memory loss, disturbance in thinking ability and eventually dementia, arising from repetitive blows to the head.
Medical scientists did not really progress this understanding until 2002 when CTE was first identified in American football players. This followed the American NFL player, Mike Webster’s, death from the disease aged 50 [7]. Further cases of CTE have been diagnosed clinically in football, rugby union, rugby league and Australian Rules Football, amongst other sports [1, 5]. The medical and sporting worlds recognise the increasing number of contact and collision sports players developing CTE.
What causes CTE?
CTE is caused by repetitive brain trauma [1, 2, 8]. In sport, this means repeated sub-concussions that transmit rotational forces to the brain.
These forces may arise from direct contact to the head, rapid acceleration or deceleration of the body, whiplash-like movement, falls, tackles, collisions, heading, or other impacts that cause the brain to rotate inside the skull [8].
The most damaging forces are rotational [8, 9]. Rotational forces cause shear strain within brain tissue, which is associated with tearing of tiny blood vessels and brain cells resulting, over time, in the breakdown of the blood-brain barrier and the creation of damaging microscopic neuro-inflammation [8, 9]. Research on repeated sub-concussive head impacts has reported measurable effects on brain health and has linked cumulative exposure with changes in cognition, brain function and neurological risk [2]. Over time, repeated exposure contributes to neuro-inflammation, abnormal protein accumulation, and progressive brain changes associated with CTE [1, 2, 8, 9].
The progressive cognitive and behavioural symptoms in CTE are the result of a complex, chronic inflammatory process, which leads to the destruction of the normal connections between the brain cells and death of the brain cells [1].
With repetitive sub-concussive impacts to the head, the most significant injury occurs to the fine blood vessels that surround brain cells. This results in damage to the blood-brain barrier, a structure designed to protect the brain [8, 9]. When this structure is damaged by repetitive trauma, an abnormal ‘immune’-mediated inflammatory response is triggered with the production of neurochemicals [1, 8, 9]. The neurochemicals and inflammatory response should be protective.
However, when the brain is subjected to repetitive impacts and before the protective neurochemicals and inflammatory changes from the initial brain injury have had time to return to normal, the subsequent, repetitive head injuries can then result in an abnormally exaggerated, further production of neurochemicals and exaggerated inflammatory response [2, 8, 9]. Instead of being protective, this is harmful to the brain. The response now damages the brain tissue and eventually leads to the irreversible death of brain cells.
Over time, repeated brain trauma is associated with abnormal changes in tau protein, one of the pathological hallmarks of CTE [1].
The tau protein which is found within cognitive brain cells normally stabilises these brain cells to ensure they work efficiently and communicate effectively with all the other cognitive brain cells, so an individual can think and behave normally [1]. When the tau protein becomes damaged, it can no longer stabilise the brain cells and the brain cells lose their ability to function efficiently and effectively [1].
Furthermore, the tau protein starts to replicate itself inside the brain cells and eventually the tau completely fills the brain cells so they burst and die [1]. Unfortunately, these brain cells cannot regenerate. The abnormal tau protein also develops the ability to “jump” from one brain cell to the next; once the abnormal tau protein enters a new brain cell, the process starts again, resulting in the death of that brain cell.
As the tau protein spreads around the brain affecting and killing more and more brain cells, needed for thinking and to control our emotions and behaviour, the symptoms of cognitive impairment and changes in behaviour become increasingly apparent. The resulting symptoms result in CTE [1, 10].
This is why Rezon focuses on brain protection in sport, not simply head protection. Traditional sports headgear is usually designed to reduce cuts, abrasions, and superficial head injury. Brain protection requires a different focus: reducing the forces transmitted to the brain, particularly rotational forces.
To understand this pathway in sport, read our detailed explanation of how repeated sub-concussive impacts and rotational forces contribute to CTE risk.
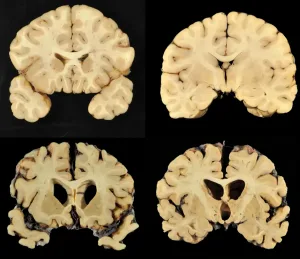
WHAT DOES A CTE BRAIN LOOK LIKE?
A CTE brain is shrunken and smaller in volume than a normal brain given the death of brain cells. While the brain shrinks to some degree in healthy ageing, it does not lose brain cells in large numbers [1]. Changes in brain tissue can be examined under the microscope after death, with the tau protein visible [1, 4].
The image below shows a normal brain (top) compared to a CTE brain (bottom).
How are repeated head impacts in sport linked to CTE?
CTE is associated with long-term exposure to repetitive head impacts. This exposure can include impacts that cause a diagnosed concussion and impacts that produce no symptoms, sub-concussions.
In sport, an important area of research is how repeated sub-concussive impacts and cumulative exposure to rotational forces contribute to the biological processes associated with long-term brain injury.
Read the full scientific explainer: CTE in Sport: How Sub-Concussions and Rotational Forces Affect the Brain.
Is CTE caused only by concussion?
No. CTE is not understood as a disease caused only by diagnosed concussion.
Peer-reviewed research describes CTE as occurring as a result of repetitive head impacts, including both concussive and sub-concussive impacts [1, 2]. A sub-concussion results from a blow or movement that transmits force to the brain but does not cause the visible clinical signs or symptoms required for a concussion diagnosis.
This is important because sub-concussions happen far more frequently than diagnosed concussions in sport [1, 2, 3]. They do not stop play, trigger medical assessment, or usually appear in injury statistics, yet they still contribute to cumulative brain loading over time.
Concussion remains serious and should always be managed medically. But the long-term brain health conversation is no longer only about recognised concussion. It is also about repeated exposure to sub-concussive head impacts that are treated currently as a routine part of sport [1, 2, 3].
What are the symptoms of CTE?
Symptoms associated with CTE can affect mood, behaviour, thinking, memory, and movement [10]. Reported symptoms may include:
- problems with memory and concentration
- confusion or impaired judgement
- mood changes, including depression or apathy
- impulsive behaviour or emotional instability
- aggression or changes in personality
- problems with movement, balance, or coordination in some cases
These symptoms can overlap with many other medical, neurological, and mental health conditions [10]. Having symptoms does not automatically mean a person has CTE. However, anyone experiencing symptoms after head injury, repeated impacts, or concussion should seek specialist medical assessment as early as possible [5, 10].
Typically, players of contact sports begin to develop symptoms in their 30s-50s, although cases have been identified in younger sports players. Early signs include mild forgetfulness, low mood, anger and slowing of thought process [5, 10].
The individual then develops physical and cognitive symptoms, such as confusion, memory loss, tremors, slurred speech, and a gradual decline in thinking ability [10]. Mood changes include aggression, depression and changes in personality. The condition eventually leads to dementia [10]. These symptoms can become debilitating and life-changing for those affected and those around them.
Symptoms of cognitive decline and subtle changes in behaviour can be very non-specific, especially in the early days of CTE [5, 10].
Can CTE be diagnosed during life?
CTE has historically been confirmed by neuropathological examination of brain tissue after death [4]. This is why many medical references describe post-mortem examination as the established method of confirmation.
However, this does not mean that living patients cannot be assessed for chronic and progressive brain injury associated with repeated head impacts. Dr Emer MacSweeney, Consultant Neuroradiologist and Rezon’s Expert Advisor, uses advanced Diffusion Tensor Imaging, or DTI, alongside MRI, specialist clinical evaluation, cognitive assessments and other tests to identify objective evidence of chronic and progressive brain injury in living patients [5].
This distinction matters. A post-mortem diagnosis confirms the pathological disease process. But specialist clinical and imaging assessment can identify evidence of brain injury during life, helping patients understand symptoms, risk, monitoring and potential intervention.
Which sports are associated with CTE risk?
CTE has been most widely studied in people with a history of repeated head impacts, including athletes in contact and collision sports and military veterans exposed to blast or impact trauma [1, 2, 3].
Sports where repetitive head impacts may occur include:
- rugby
- football
- boxing and combat sports
- AFL
- field hockey
- lacrosse
- netball and basketball collisions
- other sports involving repeated falls, tackles, or collisions
Risk is not determined by sport alone. It depends on many factors, including the number of impacts, type of impacts, age of first exposure, gender, playing position, training volume, recovery, genetics, medical history, and the cumulative magnitude of forces transmitted to the brain [1, 2].
Can CTE be prevented in sport?
No intervention can prevent CTE.
The most evidence-led approach is to reduce cumulative exposure to repetitive sub-concussions, and to reduce the rotational forces transmitted to the brain when head impacts do inevitably occur in sport [1, 2, 3, 8]. This includes better coaching, safer technique, rule changes, reduced unnecessary contact in training, improved recognition and management of concussion, appropriate recovery, and protective technologies designed around brain protection rather than superficial injury alone.
The aim is to reduce rotational force transmission to the brain during concussive and sub-concussive impacts. This was the founding principle in the design and engineering of Rezon Halos® brain protection.
How can you reduce CTE risk?
Rezon Halos® are designed to reduce rotational force transmission during concussive and sub-concussive impacts using patented Rotection® technology. Rotational forces are a key mechanism of concern in brain injury because they create shear strain inside the brain [8, 9].
No head protection can prevent CTE. CTE is a complex neurodegenerative disease linked to cumulative exposure over time [1, 2, 3]. However, reducing rotational force transmission is a rational and proactive approach to reducing one of the key mechanical risk factors associated with brain injury in sport [8, 9].
Dr. Emer MacSweeney, BSc (Hons), MRCP, FRCR and Consultant Neuroradiologist, is an expert in CTE and understanding around the impact of sub-concussions in sport [5]. Dr MacSweeney’s 2022 Ted Talk explains the importance of specialist headgear that protects the brain, not just the skull, and reduces the damage caused by rotational forces to the brain [5]. Rezon Halos® headbands for concussions and sub-concussions are proven to reduce rotational force transmission by up to 61% [11].
Reducing CTE risk requires innovation, improved education, player care and support, consideration to policy changes and game modifications and ongoing research.
Who is Most Impacted?
CTE is most commonly found in athletes, war veterans and individuals who have suffered repetitive brain traumas (including seizures, head banging behaviours, violence) [1, 2, 3, 10]. Research into football brain injuries, as well as brain injury in rugby and hockey is helping us better understand the risk of CTE in contact sports [1, 2, 3].
What Treatment is Available?
There is currently no established cure to CTE [10].
At Re:Cognition Health, under an early access drug licence, a potential treatment to halt or slow the progression of CTE symptoms is underway [5].
CTE FAQs
Here you can find answers to commonly asked questions surrounding CTE.
Summary
Rotational forces from sub-concussions increase your risk of Chronic Traumatic Encephalopathy (CTE) [1, 2, 8].
CTE is a progressive neurodegenerative brain disease caused by repetitive brain trauma, including repeated concussive and sub-concussive impacts [1, 2]. In sport, the major concern is cumulative exposure: the repeated loading of the brain over time, from impacts that do not produce symptoms [1, 2, 3].
CTE has historically been confirmed through post-mortem examination of brain tissue [4], but advanced imaging, specialist clinical evaluation and cognitive testing can identify objective evidence of chronic and progressive brain injury in living patients [5]. No single product can guarantee prevention, but reducing repeated head impacts, improving concussion management, and reducing rotational force transmission in the moment of impact are important steps in protecting long-term brain health in sport [1, 2, 3, 8, 9].
CTE is a progressive neurodegenerative disease caused by repetitive sub-concussive impacts to the brain. It is irreversible and incurable, causing life-changing physical and cognitive symptoms [1, 2, 10].
- The Neuropathology of Chronic Traumatic Encephalopathy. McKee AC et al. Brain Pathology. 2015.
- Repeated Sub-Concussive Impacts and the Negative Effects of Contact Sports on Cognition and Brain Integrity. Ntikas M, et al. International Journal of Environmental Research and Public Health, 2022.
- About Repeated Head Impacts. Centers for Disease Control and Prevention.
- NIH Chronic Traumatic Encephalopathy Diagnosis Conference. National Institute of Neurological Disorders and Stroke.
- What a world-leading Neuroradiologist wants you to know about CTE. Featuring Dr Emer MacSweeney, Consultant Neuroradiologist. Re:Cognition Health.
- History of Chronic Traumatic Encephalopathy. Cantu RC. Seminars in Neurology. 2020.
- Chronic traumatic encephalopathy in a National Football League player. Omalu BI, DeKosky ST, Minster RL, Kamboh MI, Hamilton RL, Wecht CH. Neurosurgery. 2005
- Biomechanics of Concussion. Meaney DF, Smith DH. Clinical Sports Medicine. 2011.
- Axonal Pathology in Traumatic Brain Injury. Johnson VE, Stewart W, Smith DH. Experimental Neurology. 2013.
- Chronic Traumatic Encephalopathy: Symptoms and Causes. Mayo Clinic.
Further Reading about CTE, sub-concussion and repetitive head impacts: